Reproductive health
Understanding Your Fertile Window: The Science Behind Ovulation Tracking
Work out your fertile days and ovulation date from your cycle length, then sharpen the estimate with cervical mucus, basal temperature and LH tests. Backed by peer-reviewed research.
Free online tool
Ovulation calculator
What is ovulation?
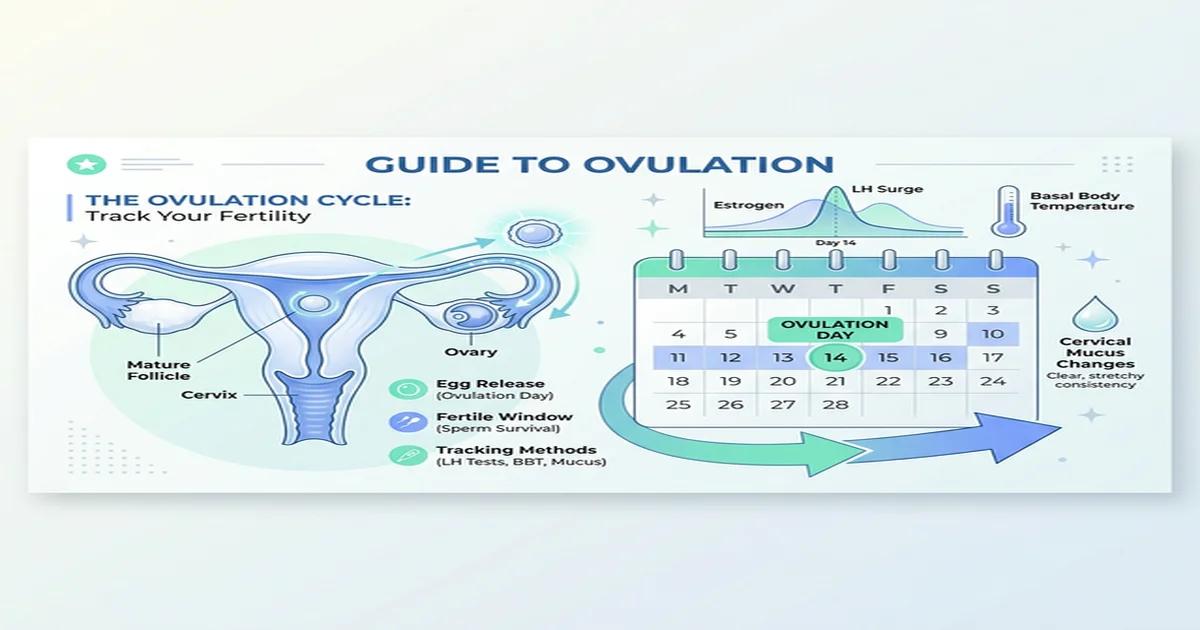
Ovulation is the release of a mature egg from one of the ovaries, typically occurring once per menstrual cycle. The egg travels through the fallopian tube where it may be fertilized by sperm. This event is the central point of the menstrual cycle and the key to understanding fertility.
During the follicular phase that precedes ovulation, rising oestrogen stimulates one dominant follicle to grow and mature the egg inside it. When oestrogen reaches a critical threshold, the pituitary gland responds with a sharp spike in luteinising hormone (LH), the LH surge, and the egg is released 24 to 36 hours later.
In a textbook 28-day cycle, ovulation occurs around day 14. However, a landmark study by Bull et al. (2019) analysing over 600,000 menstrual cycles found that only 13% of the cycles lasted exactly 28 days, and cycle lengths ranged widely from 21 to 35 days or more. This variability is entirely normal.
The calendar method: how it works
The calendar method estimates ovulation day by subtracting 14 from the total cycle length. This works because most of the variation in cycle length comes from the follicular phase, before ovulation (Fehring et al., 2006); the luteal phase — the time between ovulation and the next period — is more stable and is conventionally taken as 14 days. It is not fixed, though: in Bull et al.'s data it averaged 12.4 days, with 95% of cycles between 7 and 17 days. To find the start of your fertile window, count back five days from that estimated ovulation day.
Calendar method examples
28-day cycle
Ovulation around day 14
28 - 14 = 14. Fertile window: days 9-14.
26-day cycle
Ovulation around day 12
26 - 14 = 12. Fertile window: days 7-12.
32-day cycle
Ovulation around day 18
32 - 14 = 18. Fertile window: days 13-18.
35-day cycle
Ovulation around day 21
35 - 14 = 21. Fertile window: days 16-21.
The fertile window: 6 days that matter
Research by Dunson et al. (2002) in Human Reproduction established that the fertile window spans approximately 6 days: the 5 days before ovulation plus ovulation day itself. This is because sperm can survive in the cervical mucus and fallopian tubes for up to 5 days, while the egg remains viable for only 12 to 24 hours after release. That asymmetry is why intercourse in the days before ovulation, not just on ovulation day, can result in pregnancy.
The Wilcox et al. study showed that virtually all pregnancies result from intercourse within this six-day window, and that conception probability is not uniform across it: it rises from about 10% for intercourse five days before ovulation to about 33% on the day of ovulation itself. No pregnancies were traced to intercourse after ovulation day.
Peak fertility days
The last days before ovulation and ovulation day itself offer the highest chance of conception. If you are trying to conceive, focus on these days. If you are not, remember that this calculator is NOT a reliable contraceptive method.
The four phases of the menstrual cycle
Understanding the full cycle helps contextualise ovulation within your monthly rhythm.
- Menstrual phase (days 1-5): The uterine lining sheds, resulting in menstruation. Hormone levels are at their lowest.
- Follicular phase (days 6 to ovulation-6): Rising oestrogen stimulates follicle growth in the ovaries. One dominant follicle matures the egg for release.
- Ovulation phase (fertile window): The luteinising hormone (LH) surge triggers egg release. This is the fertile window when conception is possible.
- Luteal phase (ovulation+1 to cycle end): Progesterone rises to prepare the uterine lining for potential implantation. If no implantation occurs, hormone levels drop and a new cycle begins.
Factors that affect cycle regularity
Fehring et al. (2006) in the Journal of Obstetric, Gynecologic & Neonatal Nursing documented significant variability in menstrual cycle phases. Key factors that can shift ovulation timing include:
- Stress: Cortisol can suppress the GnRH signal that triggers ovulation, delaying or even preventing it.
- Weight changes: Both significant weight loss and gain can disrupt the hormonal balance needed for regular ovulation.
- Intense exercise: Very high training loads can suppress ovulation, a condition known as hypothalamic amenorrhea.
- Illness and travel: Fever, jet lag, and disrupted sleep can shift the follicular phase length.
- PCOS: Polycystic ovary syndrome is one of the most common causes of irregular ovulation, affecting 6-12% of reproductive-age women.
- Thyroid disorders: Both hypothyroidism and hyperthyroidism can cause irregular cycles.
- Perimenopause: The transition towards menopause is another common cause of irregular cycles.
- Medications: Hormonal contraceptives, certain antidepressants, and anti-inflammatory drugs can affect cycle timing.
If your period comes every 24 days one month and every 34 days the next, the estimated ovulation day can shift by ten days or more. In that case, track several cycles and use your shortest and longest cycle lengths to define a broader fertile window that accounts for the variability.
Limitations of the calendar method
While the calendar method is a useful starting point, it has important limitations. ACOG notes that fertility awareness-based methods have a typical-use failure rate of 12-24% when used for contraception. The calendar method alone cannot account for cycle-to-cycle variation in ovulation timing: stress, illness or hormonal fluctuations can move ovulation by several days.
For greater accuracy, many healthcare providers recommend combining the calendar method with physical fertility signs. Each one tells you something different:
Cervical mucus
As oestrogen rises in the days before ovulation, cervical mucus changes from sticky or creamy to clear, slippery, and stretchy — often compared to raw egg white. This fertile-quality mucus helps sperm travel through the cervix and survive in the reproductive tract longer. A shift to egg-white mucus is one of the earliest signs that ovulation is approaching.
Basal body temperature (BBT)
Your resting temperature rises by 0.2 to 0.5 degrees Celsius (0.4 to 1.0 degrees Fahrenheit) after ovulation due to the progesterone released by the corpus luteum. Taking your temperature every morning before getting out of bed and plotting it over several cycles reveals a biphasic pattern: lower temperatures before ovulation, higher temperatures after. The catch is that by the time the temperature shift confirms ovulation, the fertile window has already passed — so BBT is most useful for confirming that you do ovulate regularly and refining your calendar estimates for future cycles.
Ovulation predictor kits (OPKs)
OPKs are urine test strips that detect the LH surge. A positive result indicates that ovulation is likely to occur within the next 24 to 36 hours, giving couples a short but actionable heads-up. Because they detect the hormonal signal that precedes ovulation regardless of cycle length, they are especially helpful if your cycles are irregular, and they are widely available in pharmacies.
Not a contraceptive tool
This ovulation calculator is designed to help those trying to conceive. It should NOT be used as a birth control method. Consult your healthcare provider for reliable contraception.
When to see a doctor
It is normal for conception to take several cycles, even with well-timed intercourse. Consider consulting a healthcare provider or fertility specialist if:
- Your cycles are consistently shorter than 21 days or longer than 35 days, or you go months without a period.
- Your cycle length varies by more than 7-9 days from month to month.
- You have been trying to conceive for 12 months without success (or 6 months if you are 35 or older).
- You experience very painful periods, heavy bleeding, or spotting between periods.
- You have signs of hormonal imbalance such as acne, excess hair growth, or unexplained weight changes.
- You have a known condition such as PCOS, endometriosis, or thyroid disease.
- Your partner has a known or suspected male-factor issue.
A fertility specialist can run blood tests (FSH, LH, AMH, thyroid hormones), perform an ultrasound to check ovarian reserve and follicular development, and evaluate the fallopian tubes via hysterosalpingography. These tests can identify the cause of irregular ovulation or difficulty conceiving and guide targeted treatment, which may range from ovulation-induction medication to intrauterine insemination (IUI) or in-vitro fertilisation (IVF).
How to use our ovulation calculator
- Enter the first day of your last menstrual period (LMP).
- Set your average cycle length using the slider (21-35 days).
- Review your estimated ovulation date, fertile window, your next period date and your current cycle day and phase.
- Check the next 3 cycles forecast to plan ahead.
- Track your actual period start dates to refine your average cycle length over time.
Track consistently
The more cycles you track, the more accurate your average cycle length becomes. Track at least three consecutive cycles before relying on the averages, and note when your period actually starts to compare with predictions.
Sources
- Wilcox AJ et al. Timing of sexual intercourse in relation to ovulation. NEJM. 1995;333(23):1517-21
- Dunson DB et al. Changes with age in the level and duration of fertility in the menstrual cycle. Human Reproduction. 2002;17(5):1399-403
- Fehring RJ et al. Variability in the phases of the menstrual cycle. JOGNN. 2006;35(3):376-84
- ACOG Committee Opinion 700: Methods for Estimating the Due Date. Obstet Gynecol. 2017;129(5):e150-e154.
- ACOG FAQ: Fertility Awareness-Based Methods of Family Planning.
- Bull JR et al. Real-world menstrual cycle characteristics of more than 600,000 menstrual cycles. NPJ Digital Medicine. 2019;2:83